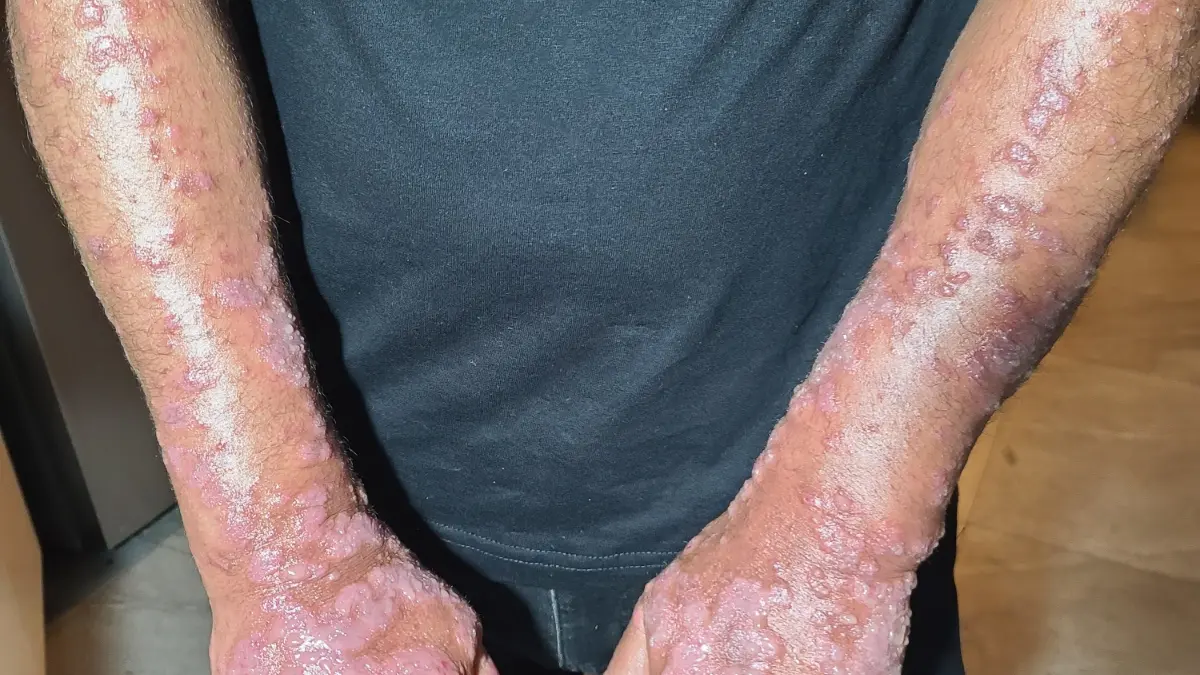

Bottom line: A rash is a symptom, not one diagnosis. Essential oils are not a safe general treatment because the wrong product may irritate the skin, trigger allergy or obscure an infection that needs different care.
Call 999 for a rash with breathing difficulty, swelling of the mouth or throat, collapse or severe confusion. Seek urgent advice for a non-fading rash with fever or a rapidly worsening, painful or blistering rash.
Why the cause matters
Rashes can result from eczema, contact allergy, infection, medicines, heat, bites, autoimmune disease and many other causes. Their treatments are not interchangeable.
Contact dermatitis often produces itchy, dry, cracked or blistered skin after contact with an irritant or allergen. The NHS recommends assessment when symptoms are persistent, recurrent or severe.
Ringworm needs antifungal treatment. Hives may respond to an antihistamine. A painful spreading bacterial infection can need antibiotics. Adding fragrance before identifying the problem may make both diagnosis and treatment harder.
What research on essential oils can and cannot show
Tea tree, lavender and chamomile are frequently promoted for rashes. Laboratory anti-inflammatory or antimicrobial activity may justify further research, but it does not establish treatment for an unexplained human rash.
One small experiment tested tea tree oil on nickel-induced contact reactions in 27 volunteers. It reported reduced skin response, but this artificial model was not a trial of eczema, infection or an undiagnosed rash.
The result also sits beside evidence that tea tree oil can cause dermatitis. A substance may have an effect in one controlled experiment and still be unsuitable as a general skin treatment.
Clinicians have reported allergic contact dermatitis after tea tree products were used on lips and toenails. A case report cannot measure risk, but it demonstrates the opposite of a universally soothing effect.
Another report describes a widespread allergic eruption after a tea tree lotion was applied to a wart. The reaction resolved after the product was stopped and medical treatment was given.
Fragrance allergy is relevant
Many essential oils contain limonene, linalool and related fragrance compounds. Exposure to air can create oxidation products that are more likely to sensitise susceptible skin.
A 2024 review of fragrance contact allergy explains why oxidised terpenes matter in patch testing. The evidence concerns allergy diagnosis, not proof that every user will react.
A broader review found that many essential oils have caused contact allergy. Tea tree, citronella, ylang-ylang, sandalwood, clove and orange were among oils with notable patch-test reactions.
DermNet advises against applying neat essential oils to skin. It also notes that allergic dermatitis may extend beyond the area where the product was applied.
What to do with a new rash
Stop any new fragranced oil, cosmetic, detergent or topical remedy that might be involved. Avoid repeatedly testing the suspected product on already inflamed skin.
Use gentle washing and avoid scratching. A pharmacist can advise about simple symptom relief, but the treatment depends on the likely cause and the part of the body affected.
NHS contact-dermatitis guidance prioritises avoiding the trigger and using suitable emollients. A clinician may prescribe a topical corticosteroid when appropriate.
Take clear photographs if the appearance changes. Note new medicines, illnesses, foods and skin products. Do not stop prescribed medicine without professional advice.
Record where the rash started and whether it moves, scales, blisters or fades under pressure. Timing after a new exposure can help, although timing alone cannot identify the cause.
If a clinician suspects allergic contact dermatitis, patch testing may identify a specific allergen. This formal test is different from applying a consumer product to irritated skin at home.
When a rash needs urgent assessment
Call 999 if a rash accompanies breathing difficulty, throat tightness, swelling of the tongue or lips, severe dizziness or collapse. These may be signs of anaphylaxis.
Use a clear glass to check a red or purple rash that may not fade under pressure. A non-fading rash with fever or illness needs urgent medical help.
Seek prompt advice for extensive blistering, skin peeling, severe pain, fever, facial swelling or a rash following a new medicine. Babies and immunocompromised people may need earlier assessment.
A rash around the eyes, inside the mouth or on the genitals may require tailored treatment. Do not place essential oils on these sensitive areas.
Seven oil-specific rash claims: why the diagnosis changes the evidence
The same oil may have a favourable result for one defined condition and a negative result or an allergy report in another setting. These comparisons add the individual studies to the diagnostic and urgent-care advice above.
Cedarwood and rashes
No controlled human study establishing cedarwood oil as a treatment for undiagnosed rashes was located. A single acne case report described improvement when cedarwood was added to care. An uncontrolled observation cannot separate the oil’s contribution from other treatment or natural fluctuation, and acne is not a synonym for rash.
A 1998 report describes allergic contact dermatitis after cedarwood oil was used during dermatoscopy. Only the indexed bibliographic record was available here, so the precise exposure and test results cannot be evaluated.
In a 13-week toxicology experiment, repeated Virginia cedarwood oil applications produced skin lesions in rats and mice. Those exposure conditions do not supply a human safe-use threshold, but they contradict a claim that the oil is intrinsically non-irritating. Cedarwood products can come from different botanical species. Neither one acne report nor a laboratory antimicrobial effect justifies treating an unexplained rash with them.
Related: Cedarwood profile.
Geranium and rashes
A geranium-oil experiment reduced acute swelling and skin inflammation in mice. Cultured human fibroblast research also found biological activity. Neither study treated people with an unexplained rash.
These distinctions matter because allergic dermatitis, fungal infection and hives do not share a single treatment. Reducing an inflammatory laboratory measurement cannot show that an oil removes the cause of a rash. Suppressing cultured-cell proliferation also does not establish healthy skin repair.
No controlled human geranium-oil rash-treatment trial was located in the targeted search. The useful next step for a recurrent rash is to identify its cause and review recent products, rather than to choose geranium because an advertisement calls it anti-inflammatory. If the rash appeared after a scented product, adding another fragrance may complicate that assessment.
Related: Geranium profile.
Lavender and rashes
A lavender study used a keratinocyte reporter model of a pathway relevant to atopic dermatitis. Its favourable cell results and sensitisation assays cannot establish that lavender treats patients’ rashes or never causes allergy.
Actual clinic data provide a necessary counterpoint. In a retrospective Australian patch-test series, 49 of 2,178 people tested reacted to lavender, and 27 were diagnosed with allergic contact dermatitis. These were selected clinic patients, so the figures are not population risks.
A 2026 pilot study in 18 people with psoriasis and chronic kidney disease reported improved skin scores after 60 days. However, it used an extract prepared after removal of the volatile oil, and had no control group. It therefore cannot establish either an essential-oil effect or treatment for rashes generally. Lavender’s scent and traditional reputation should not override the diagnosis or a history of reacting to fragranced products.
Related: Lavender profile.
Myrrh and rashes
Myrrh reduced histamine and an itch-related cytokine in stimulated human mast cells. This is a laboratory mechanism, not a measurement of symptom relief in people. A further extract study in mast-cell-like cells found effects dependent on how the cells were stimulated: there was no effect after one chemical stimulation protocol. Neither experiment measured rash clearance.
A rash may itch for many reasons, including infection or a reaction to a medicine. Even reliable itch relief would not demonstrate that its underlying cause had been treated. The targeted search did not locate a controlled human trial establishing myrrh essential oil as a general rash treatment.
Two published reports identify allergic contact dermatitis associated with myrrh. Their indexed records were available, but not sufficient detail for a full case appraisal or risk estimate. They still make a universal claim that myrrh soothes inflamed skin untenable. Resin, water or ethanol extracts and distilled oil should not be treated as interchangeable preparations.
Related: Myrrh profile.
Rosemary and rashes
A randomised trial enrolled 42 people with scalp seborrhoeic dermatitis and compared a manufactured rosemary lotion with ketoconazole for two months. Thirty-nine completed and were analysed. Ketoconazole reduced scaling more; rosemary reduced itching more. Quality-of-life improvement did not significantly differ between groups.
Two rosemary users withdrew because of burning and itching. The study was small, and its defined scalp condition and lotion cannot represent all rashes or every retail essential oil. The paper calls the product a rosemary extract lotion; the formulation’s identity matters when applying its findings.
An earlier experimental irritant-dermatitis study tested rosemary-extract creams in healthy volunteers. Some measurements suggested protection during irritant exposure, but advantages over the cream control were not statistically significant, and treatment after irritation had no effect. These limiting findings should accompany any claim of protection.
Rosemary essential-oil findings in a mouse dermatitis model remain preclinical. A contact-allergy report involving rosemary leaf extract in a cleansing gel also shows why botanical origin is not a guarantee of tolerance.
Related: Rosemary profile.
Sandalwood and rashes
A randomised, investigator-blinded study of 40 women receiving breast radiotherapy compared a turmeric-and-sandalwood cream with baby oil over five weeks. The combination delayed or reduced radiation dermatitis at some assessments. It contained both turmeric extract and sandalwood oil, so the result cannot identify sandalwood’s individual effect.
An earlier 50-person head-and-neck radiotherapy trial also favoured the same combination over baby oil, including fewer severe reactions. It likewise could not isolate sandalwood. The breast trial was small, used an active comparator and did not fully blind participants. There is also a numerical reporting inconsistency: one percentage does not match its accompanying numerator and denominator. These limitations weaken the precision of the estimate. Radiation-related skin injury is a specialised setting; an oncology team should decide which products are appropriate during treatment.
Evidence from this combination cannot establish treatment for hives, infection, medicine reactions or other unexplained rashes. Dermatology patch-test data also include sandalwood allergy. Those clinic results do not estimate risk in all users, but they rule out assuming that sandalwood is harmless simply because it is botanical.
Related: Sandalwood profile.
Tea tree and rashes
The experimental contact-dermatitis study discussed above had mixed findings. Tea tree reduced the nickel-allergy skin response, but the pretreatments did not improve irritant dermatitis, non-immunological contact urticaria or histamine-induced itch. It is misleading to turn its favourable nickel result into a treatment for every rash.
Specific diagnoses have separate clinical evidence. A 126-person dandruff trial found better overall scores with tea tree shampoo, although participants’ own scaliness ratings did not improve significantly compared with placebo.
For athlete’s foot, a trial with 104 completers found that 10% tea tree cream improved symptoms but did not clear fungal cultures significantly better than placebo; tolnaftate performed better for fungal clearance. A later 158-person trial reported better clinical responses with stronger tea tree solutions and better fungal clearance in the 50% group than placebo, but four tea tree users developed moderate-to-severe dermatitis.
These concentrations describe research products, not home-mixing instructions. Symptom relief, fungal eradication and tolerability are different outcomes. A spreading allergic reaction after a tea tree wart product further illustrates why treating an unidentified eruption with the oil can make matters worse.
Related: Tea tree profile.
Care in context
For persistent, recurrent or severe dermatitis, NHS guidance recommends assessment and identification of triggers. The warning signs earlier on this page still apply. Formal clinician-arranged patch testing is different from trying an oil on inflamed skin at home.
Search limitations: Targeted Europe PMC and web searches combined common and botanical plant names with the relevant skin condition, clinical trial, dermatitis, rash and wrinkle terms, with narrower follow-up searches and citation checks, completed 16 September 2026. This is an editorial review, not a systematic review or a complete unpublished-trial search. Indexed abstracts were used where full texts were unavailable; bibliographic-only allergy reports are identified in the text. Failure to locate a trial does not prove that none exists. Full texts were checked for the rosemary scalp trial, lavender cell and clinical pilot studies, sandalwood/turmeric radiotherapy trial and small carrot cream report. The carrot nanoemulgel author-posted report was checked. Other studies were appraised from indexed abstracts or explicitly limited bibliographic records. Product identity and inconsistent reporting limit several cosmetic studies.
Facial flushing and scaly plaques need different assessment
Rosacea and psoriasis have different clinical patterns and treatment pathways. Neither can be diagnosed simply from the word “rash”.
Fragranced oils may add irritation or allergy to the original symptoms. Eye pain or visual changes with facial symptoms, or rapidly worsening extensive skin disease with illness, call for prompt medical assessment rather than a stronger home mixture.
Targeted evidence update: 12 September 2026. This addition does not represent a new review of every statement on this page.
Peppermint has small human itch studies, not a general rash cure
Evidence update: 14 September 2026.
A 50-person study reported improved chronic itching with topical peppermint. A burn-scar study used a combined hydrogel, so its findings cannot be assigned to peppermint alone or applied to fresh burns. Itch relief does not treat every underlying cause.
Coconut neonatal research concerns supervised skin care
A 72-infant trial reported better skin condition with coconut oil but no significant difference in common neonatal outcomes, including sepsis. The Cochrane emollient review found low-certainty infection evidence across several oils. These findings do not establish treatment for every baby rash.
My verdict
There is no evidence-based essential-oil treatment for “rashes” as a group. A narrow experimental result cannot overcome the fact that different rashes have different causes and some oils are established allergens.
Identify the likely cause, stop possible irritants and use condition-specific advice. If the rash is severe, spreading or accompanied by systemic symptoms, seek medical help rather than adding another topical product.
Related evidence review: Essential Oils for Rosacea: Evidence, Irritation and Safer Care.
Related evidence review: Essential Oils for Psoriasis: What Human Studies Do and Do Not Show.
Related evidence review: Chamomile Oil for Eczema: Cream Trials, Allergy and Evidence Limits.
Related evidence review: Sandalwood Oil for Eczema: The Pilot Study and the Placebo-Controlled Results.
Related evidence review: Tea Tree Oil for Eczema: What the Contact Dermatitis Studies Actually Show.
Related evidence review: Peppermint Oil for Itching and Rashes: Human Studies and Safety.
Related evidence review: Coconut Oil for Baby Skin: Premature-Infant Trials and Safety.
Related evidence review: Coconut oil: eczema evidence and other rashes.
References
- Franz H, Frank R, Rytter M, Haustein UF. Allergic contact dermatitis due to cedarwood oil after dermatoscopy. Contact dermatitis. 1998;38:182-183. DOI:10.1111/j.1600-0536.1998.tb05701.x.
- Catlin NR, Herbert R, Janardhan K, Hejtmancik MR, Fomby LM, Vallant M, Kissling GE, DeVito MJ. Dose-response assessment of the dermal toxicity of Virginia cedarwood oil in F344/N rats and B6C3F1/N mice. Food and chemical toxicology : an international journal published for the British Industrial Biological Research Association. 2016;98:159-168. DOI:10.1016/j.fct.2016.10.016.
- Hassoun LA, Ornelas JN, Sivamani RK. Cedarwood Oil as Complementary Treatment in Refractory Acne. Journal of alternative and complementary medicine (New York, N.Y.). 2016;22:252-253. DOI:10.1089/acm.2015.0208.
- Boukhatem MN, Kameli A, Ferhat MA, Saidi F, Mekarnia M. Rose geranium essential oil as a source of new and safe anti-inflammatory drugs. The Libyan journal of medicine. 2013;8:22520. DOI:10.3402/ljm.v8i0.22520.
- Han X, Beaumont C, Stevens N. Chemical composition analysis and in vitro biological activities of ten essential oils in human skin cells. Biochimie open. 2017;5:1-7. DOI:10.1016/j.biopen.2017.04.001.
- Sato H, Kato K, Koreishi M, Nakamura Y, Tsujino Y, Satoh A. Aromatic oil from lavender as an atopic dermatitis suppressant. PloS one. 2024;19:e0296408. DOI:10.1371/journal.pone.0296408.
- Bingham LJ, Tam MM, Palmer AM, Cahill JL, Nixon RL. Contact allergy and allergic contact dermatitis caused by lavender: A retrospective study from an Australian clinic. Contact dermatitis. 2019;81:37-42. DOI:10.1111/cod.13247.
- Moisa C, Rațiu IA, Topală A, Gîrbu V, Arîcu A, Kulcițki V, Cacuci M, Rațiu CA, Maghiar L, Maghiar TA, Ganea M. Prospective Pilot Study of Lavender Terpenoid Topical Formulation in Psoriasis Patients with Chronic Kidney Disease: Clinical and Inflammatory Outcomes. Biomedicines. 2026;14:552. DOI:10.3390/biomedicines14030552.
- Shin JY, Che DN, Cho BO, Kang HJ, Kim J, Jang SI. Commiphora myrrha inhibits itch-associated histamine and IL-31 production in stimulated mast cells. Experimental and therapeutic medicine. 2019;18:1914-1920. DOI:10.3892/etm.2019.7721.
- Altenbernd F, Schwarz L, Lipowicz B, Vissiennon C. Myrrh and Chamomile Flower Extract Inhibit Mediator Release from IgE-stimulated Mast-Cell-Like RBL-2H3 Cells. Plants (Basel, Switzerland). 2022;11:3422. DOI:10.3390/plants11243422.
- Al-Suwaidan SN, Gad el Rab MO, Al-Fakhiry S, Al Hoqail IA, Al-Maziad A, Sherif AB. Allergic contact dermatitis from myrrh, a topical herbal medicine used to promote healing. Contact dermatitis. 1998;39:137. DOI:10.1111/j.1600-0536.1998.tb05867.x.
- Gallo R, Rivara G, Cattarini G, Cozzani E, Guarrera M. Allergic contact dermatitis from myrrh. Contact dermatitis. 1999;41:230-231. DOI:10.1111/j.1600-0536.1999.tb06143.x.
- Sadati MS, Alesana F, Hekmat M, Parvizi MM. Efficacy of Topical Rosemary Extract Lotion versus Topical 2% Ketoconazole Lotion in the Treatment of Seborrheic Dermatitis: A Double-Blind Randomized Controlled Clinical Trial. Dermatology practical & conceptual. 2024;14:. DOI:10.5826/dpc.1404a242.
- Fuchs SM, Schliemann-Willers S, Fischer TW, Elsner P. Protective effects of different marigold (Calendula officinalis L.) and rosemary cream preparations against sodium-lauryl-sulfate-induced irritant contact dermatitis. Skin pharmacology and physiology. 2005;18:195-200. DOI:10.1159/000085865.
- Li J, Duan J, Wang Y, Zhou P, Wang X, Xia N, Wang J, Li J, Wang W, Wang X, Sun J, Guo D, Zou J, Zhang X, Wang C. The JAK/STAT/NF-κB signaling pathway can be regulated by rosemary essential oil, thereby providing a potential treatment for DNCB-induced in mice. Biomedicine & pharmacotherapy = Biomedecine & pharmacotherapie. 2023;168:115727. DOI:10.1016/j.biopha.2023.115727.
- Inui S, Katayama I. Allergic contact dermatitis induced by rosemary leaf extract in a cleansing gel. The Journal of dermatology. 2005;32:667-669. DOI:10.1111/j.1346-8138.2005.tb00819.x.
- Rao S, Hegde SK, Baliga-Rao MP, Lobo J, Palatty PL, George T, Baliga MS. Sandalwood Oil and Turmeric-Based Cream Prevents Ionizing Radiation-Induced Dermatitis in Breast Cancer Patients: Clinical Study. Medicines (Basel, Switzerland). 2017;4:E43. DOI:10.3390/medicines4030043.
- Palatty PL, Azmidah A, Rao S, Jayachander D, Thilakchand KR, Rai MP, Haniadka R, Simon P, Ravi R, Jimmy R, D’souza PF, Fayad R, Baliga MS. Topical application of a sandal wood oil and turmeric based cream prevents radiodermatitis in head and neck cancer patients undergoing external beam radiotherapy: a pilot study. The British journal of radiology. 2014;87:20130490. DOI:10.1259/bjr.20130490.
- Geier J, Schubert S, Reich K, Skudlik C, Ballmer-Weber B, Brehler R, Weisshaar E, Uter W, IVDK. Contact sensitization to essential oils: IVDK data of the years 2010-2019. Contact dermatitis. 2022;87:71-80. DOI:10.1111/cod.14126.
- Wallengren J. Tea tree oil attenuates experimental contact dermatitis. Archives of dermatological research. 2011;303:333-338. DOI:10.1007/s00403-010-1083-y.
- Satchell AC, Saurajen A, Bell C, Barnetson RS. Treatment of dandruff with 5% tea tree oil shampoo. Journal of the American Academy of Dermatology. 2002;47:852-855. DOI:10.1067/mjd.2002.122734.
- Tong MM, Altman PM, Barnetson RS. Tea tree oil in the treatment of tinea pedis. The Australasian journal of dermatology. 1992;33:145-149. DOI:10.1111/j.1440-0960.1992.tb00103.x.
- Satchell AC, Saurajen A, Bell C, Barnetson RS. Treatment of interdigital tinea pedis with 25% and 50% tea tree oil solution: a randomized, placebo-controlled, blinded study. The Australasian journal of dermatology. 2002;43:175-178. DOI:10.1046/j.1440-0960.2002.00590.x.
- Ambrogio F, Foti C, Cazzato G, Mortato E, Mazzoccoli S, De Caro AP, Cassano N, Vena GA, Calogiuri G, Romita P. Spreading Allergic Contact Dermatitis to Tea Tree Oil in an Over-the-Counter Product Applied on a Wart. Medicina (Kaunas, Lithuania). 2022;58:561. DOI:10.3390/medicina58050561.
- NHS. Rashes care guidance. Accessed 16 September 2026.
- NHS: Treating contact dermatitis
- British Association of Dermatologists: Contact dermatitis
- DermNet: Allergic contact dermatitis to essential oils
- de Groot and Schmidt: Essential oils and contact allergy
- Sukakul and colleagues: Fragrance contact allergy review
- Lauriola and colleagues: Tea tree oil contact dermatitis
- Posadzki and colleagues: Adverse effects of aromatherapy